Orbital Calcifications
Practical approach: Localize the calcium precisely, then integrate patient age, morphology, an associated mass, bone response, and clinical history. CT with thin sections and soft-tissue and bone windows is most sensitive for calcium, foreign material, and osseous change. MRI complements CT when soft-tissue origin, optic-pathway extension, hemorrhage, or perineural disease must be defined.
Reference Images
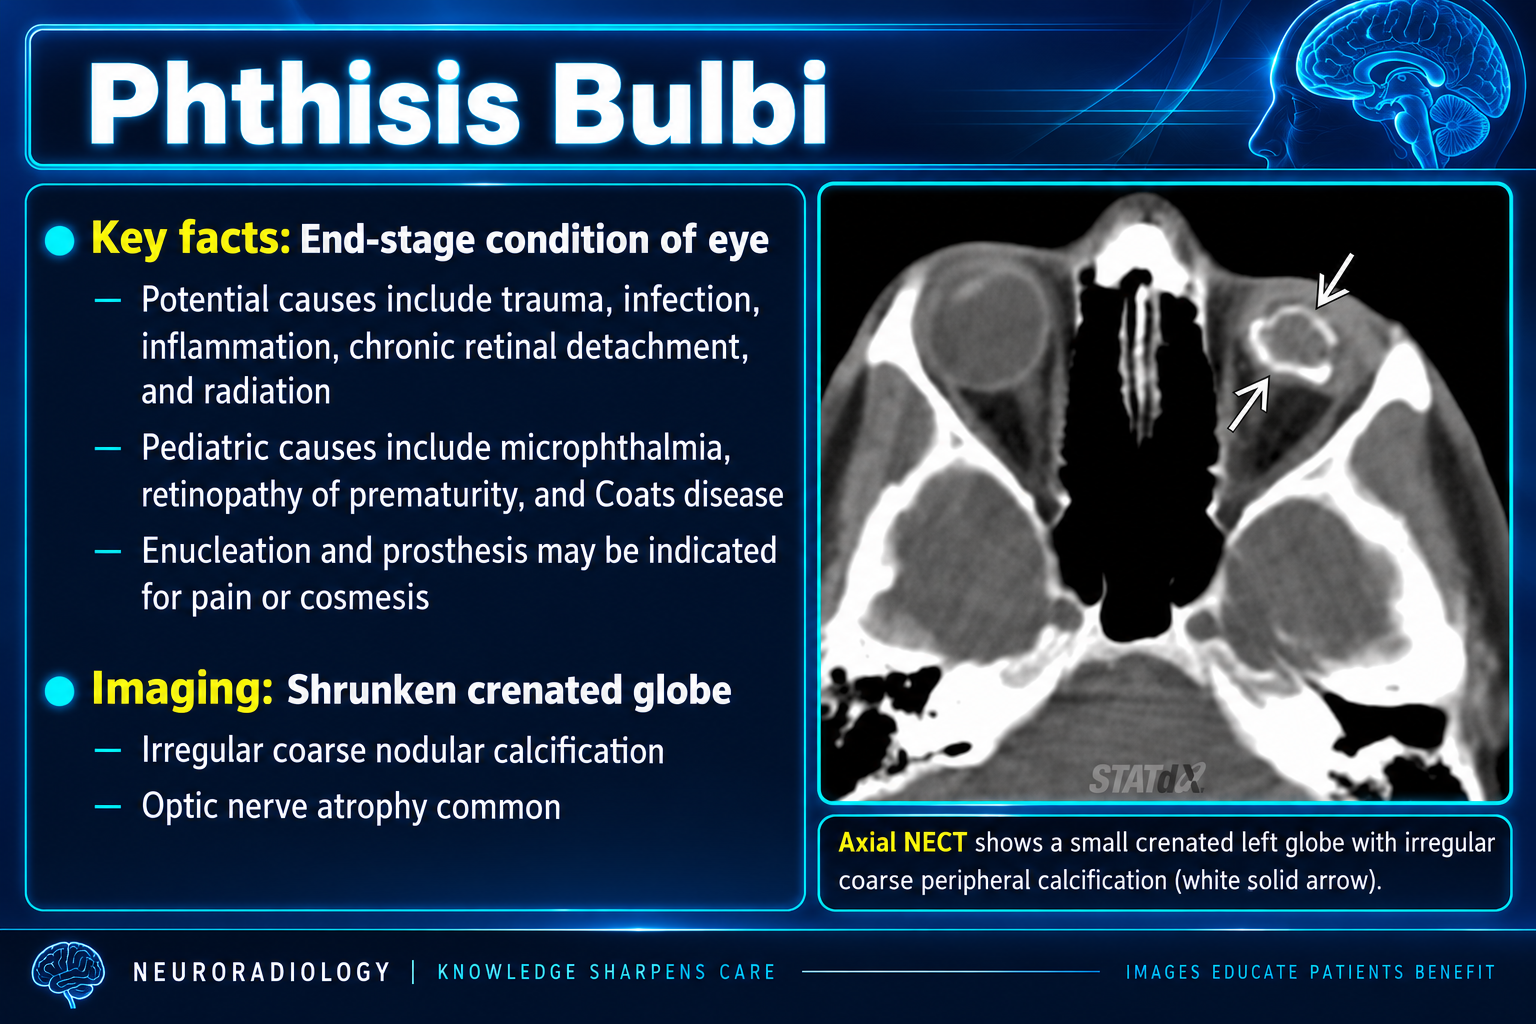
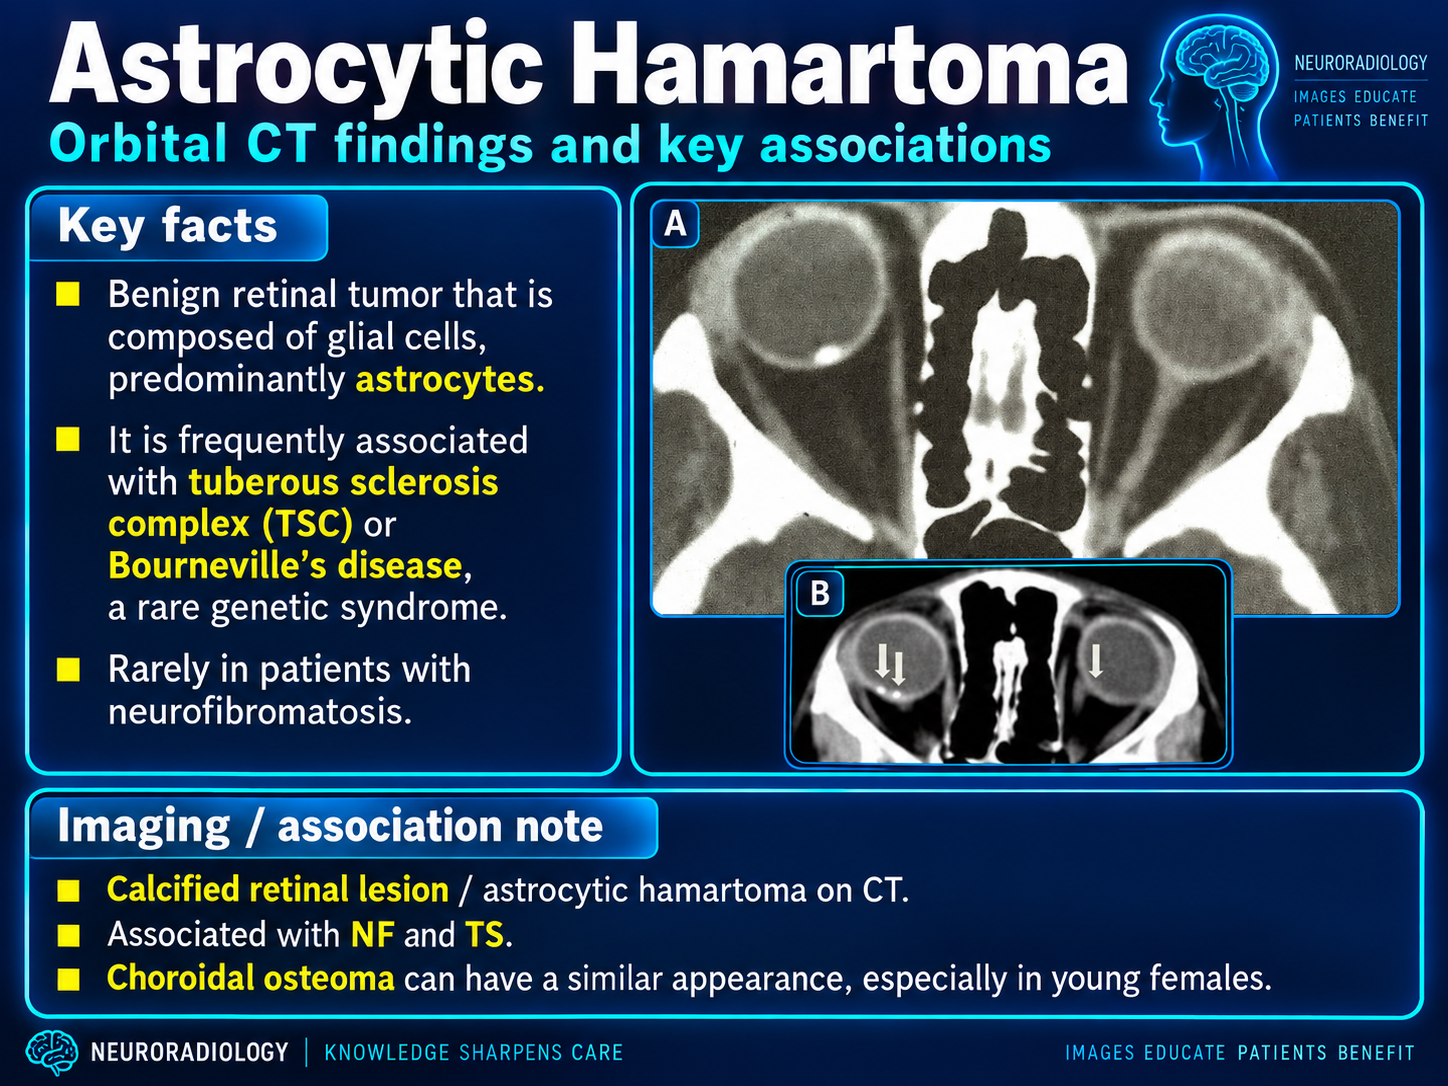
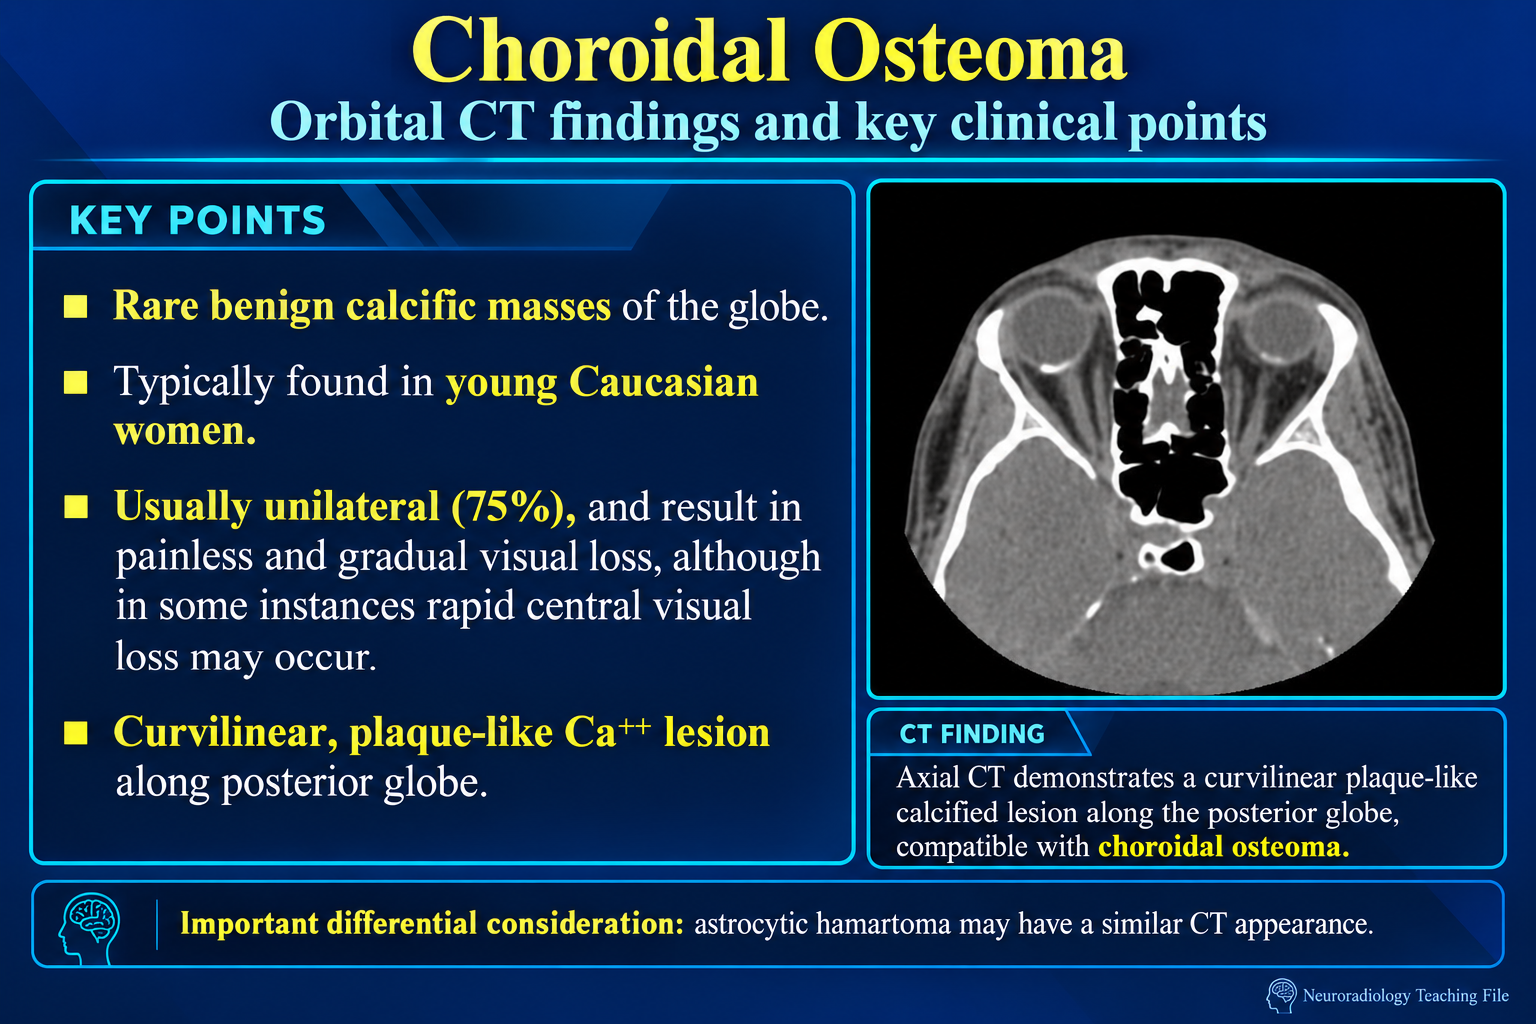
Globe Differential
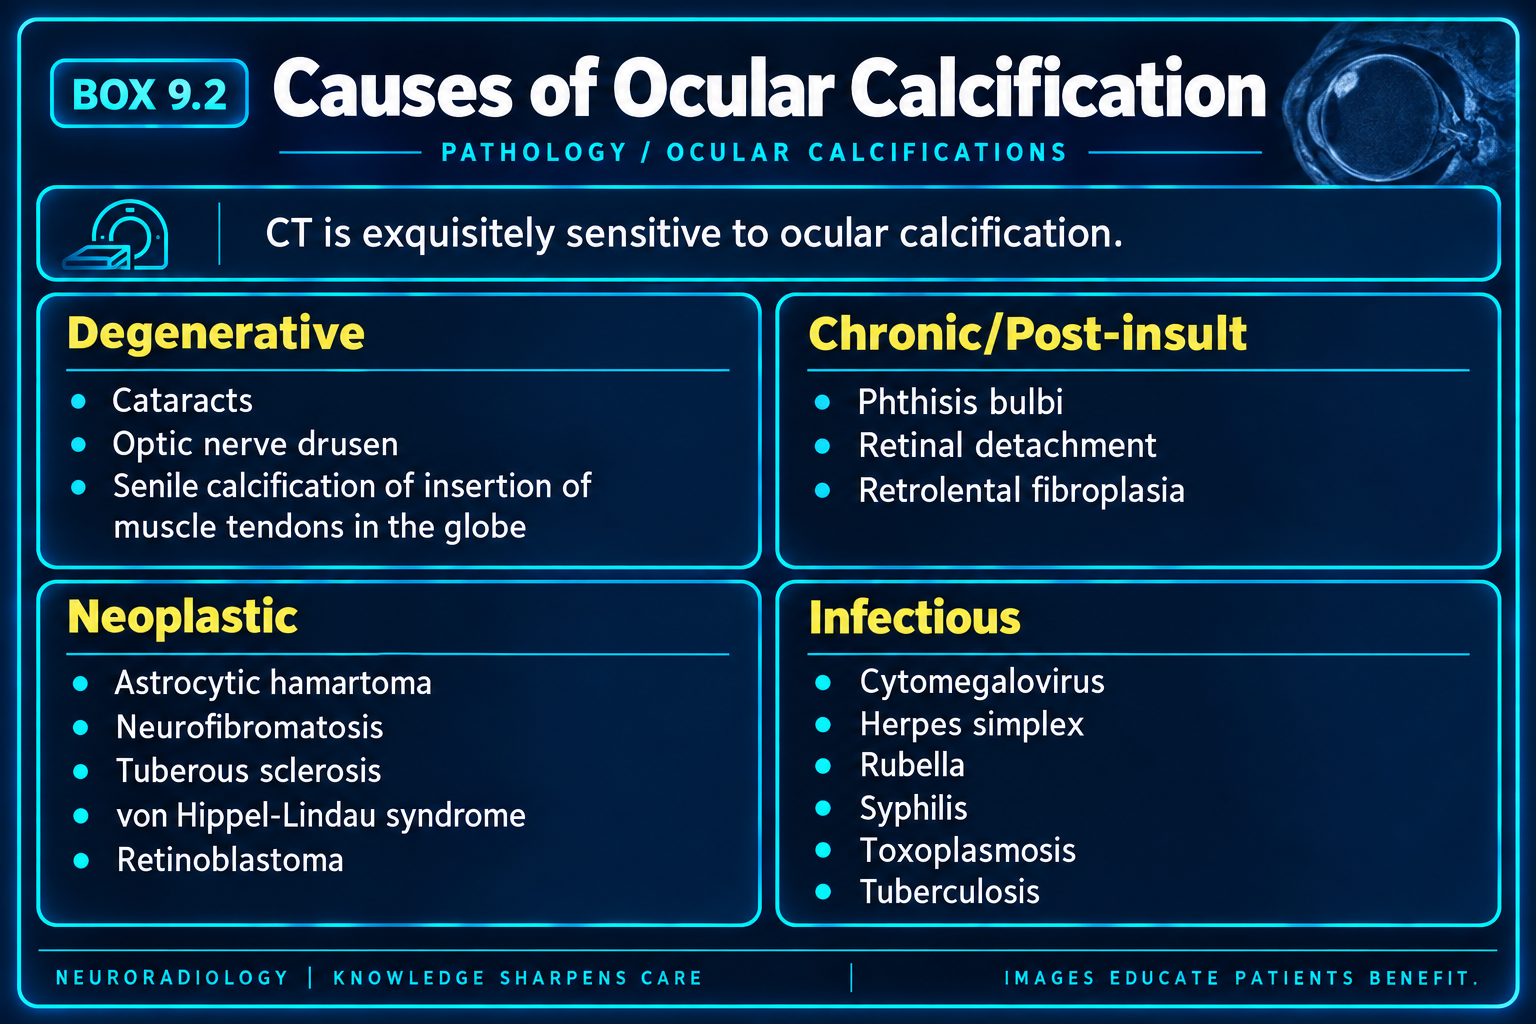
Posterior globe calciumCT cannot reliably separate scleral, choroidal, and retinal layers. Use location, age, morphology, and associated findings.
Retinal
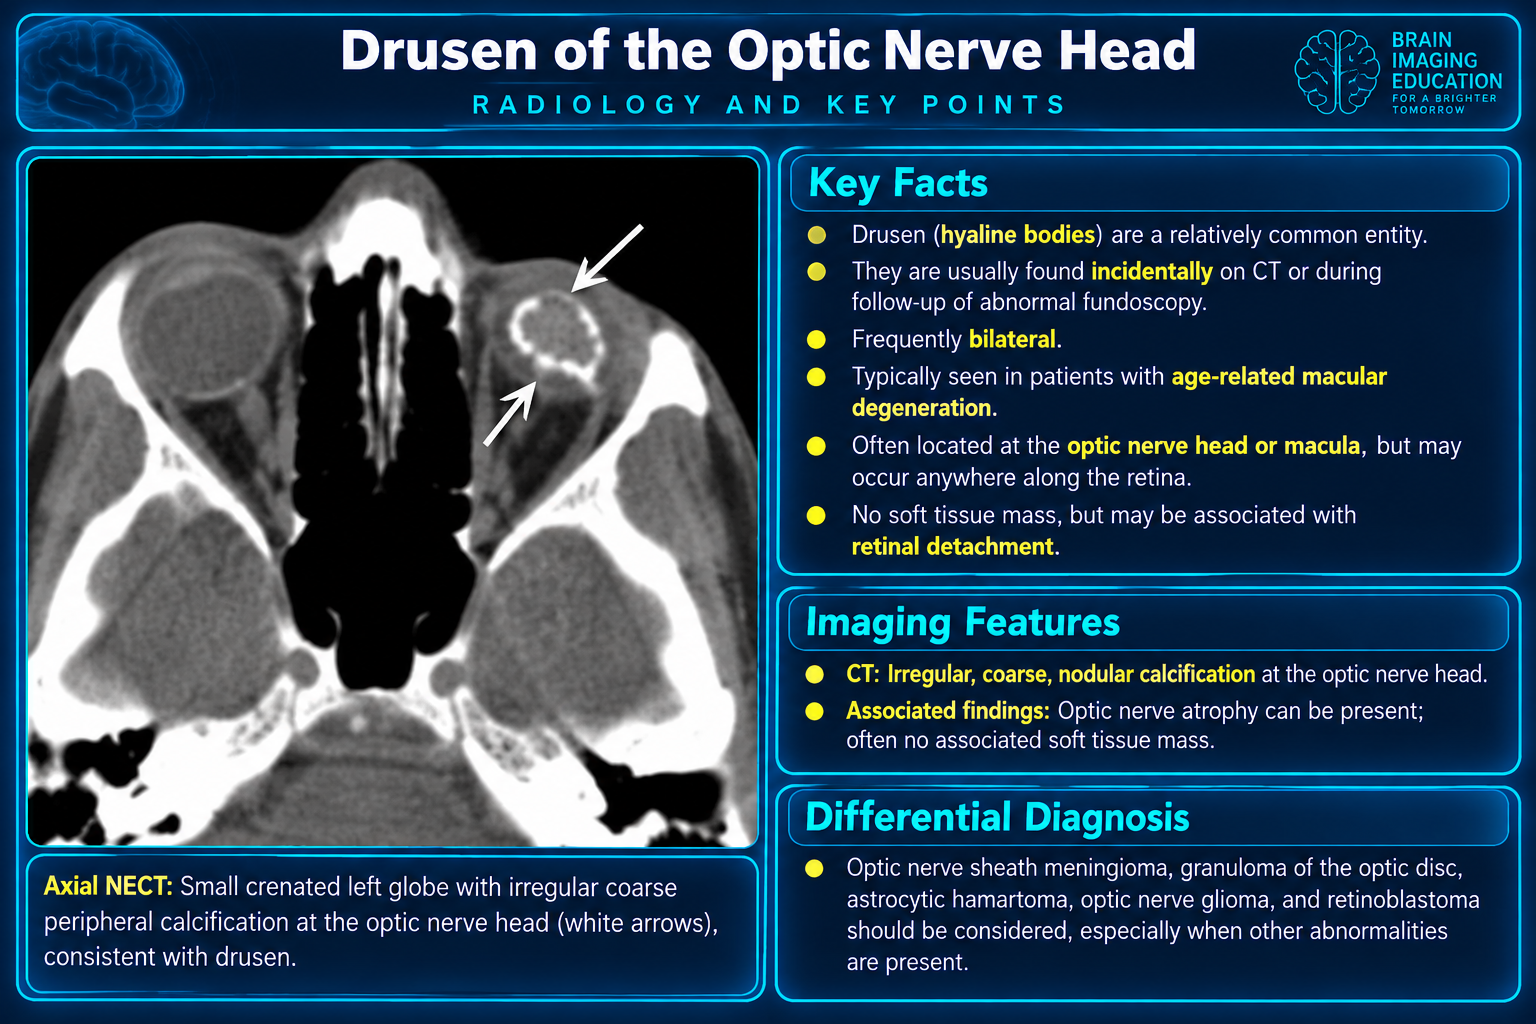
- Drusen: typically benign calcification at the optic disc.
- Retinoblastoma: calcified enhancing retinal mass in a child.
- Retinocytoma.
- Tuberous sclerosis: calcified astrocytic hamartomas or “giant drusen.”
- Epiretinal membranes.
- Retrolental fibroplasia and Coats disease.
Retinochoroidal and choroidal
- Chorioretinitis, commonly after toxoplasmosis.
- Choroidal osteoma: plaque-like bone-density lesion, often juxtapapillary.
- Choroidal angioma and choroidal nevus may calcify.
Benign and Systemic Patterns
Classic incidental sites
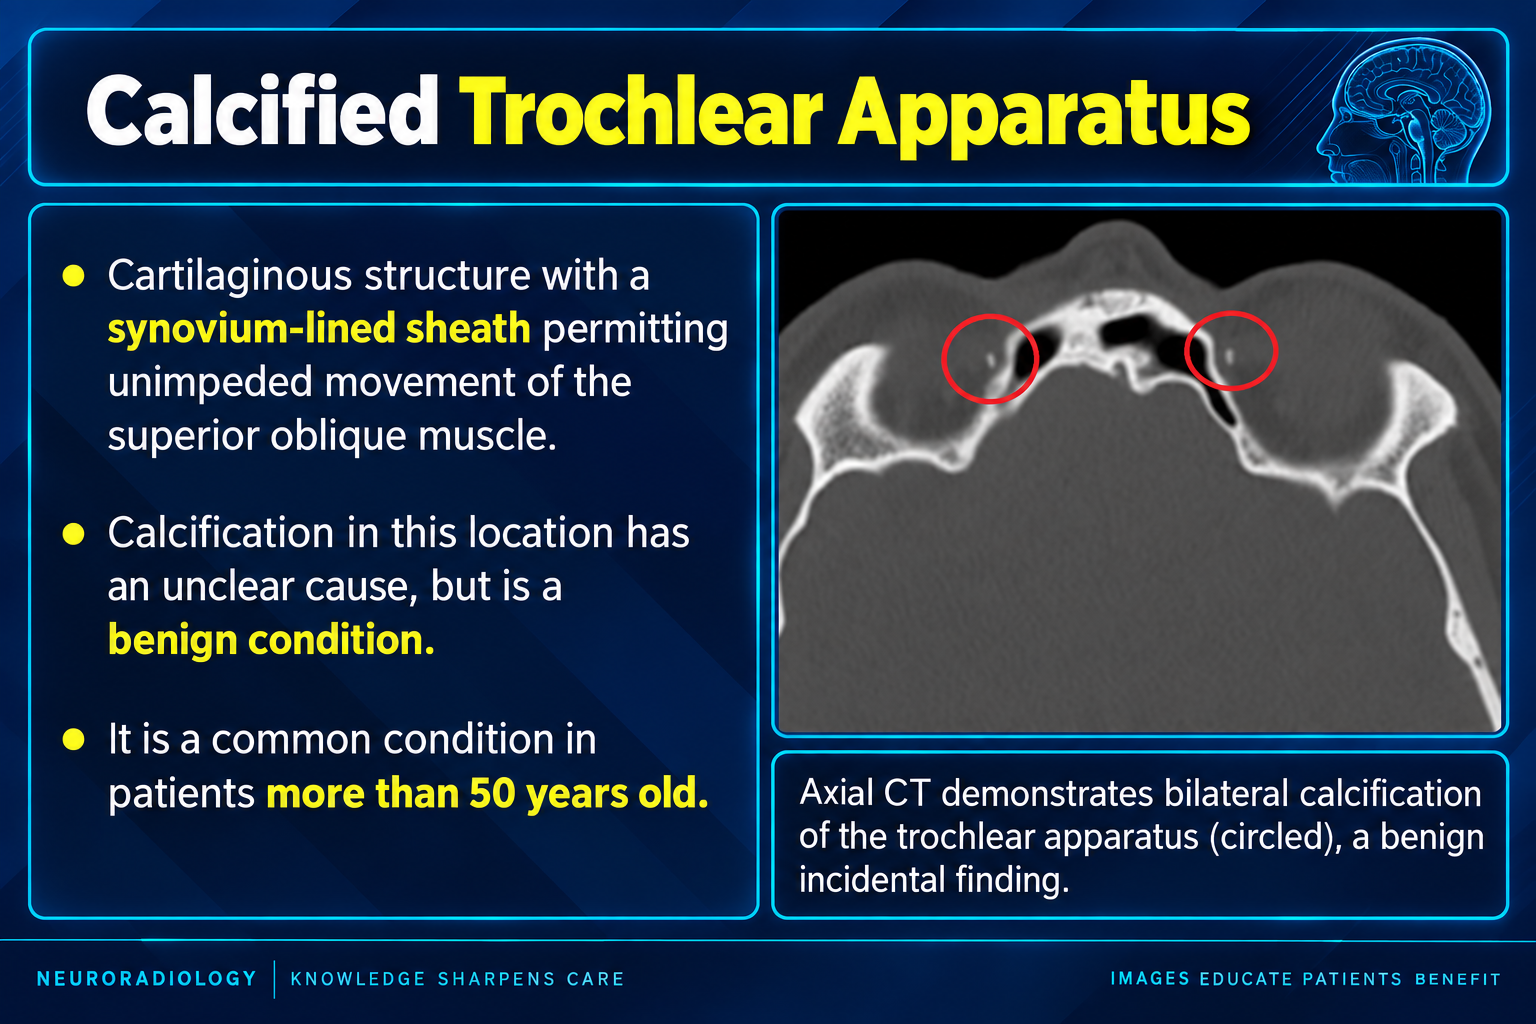
- Trochlear apparatus: small linear, curvilinear, or nodular focus at the superomedial orbit; usually incidental and may mimic a foreign body.
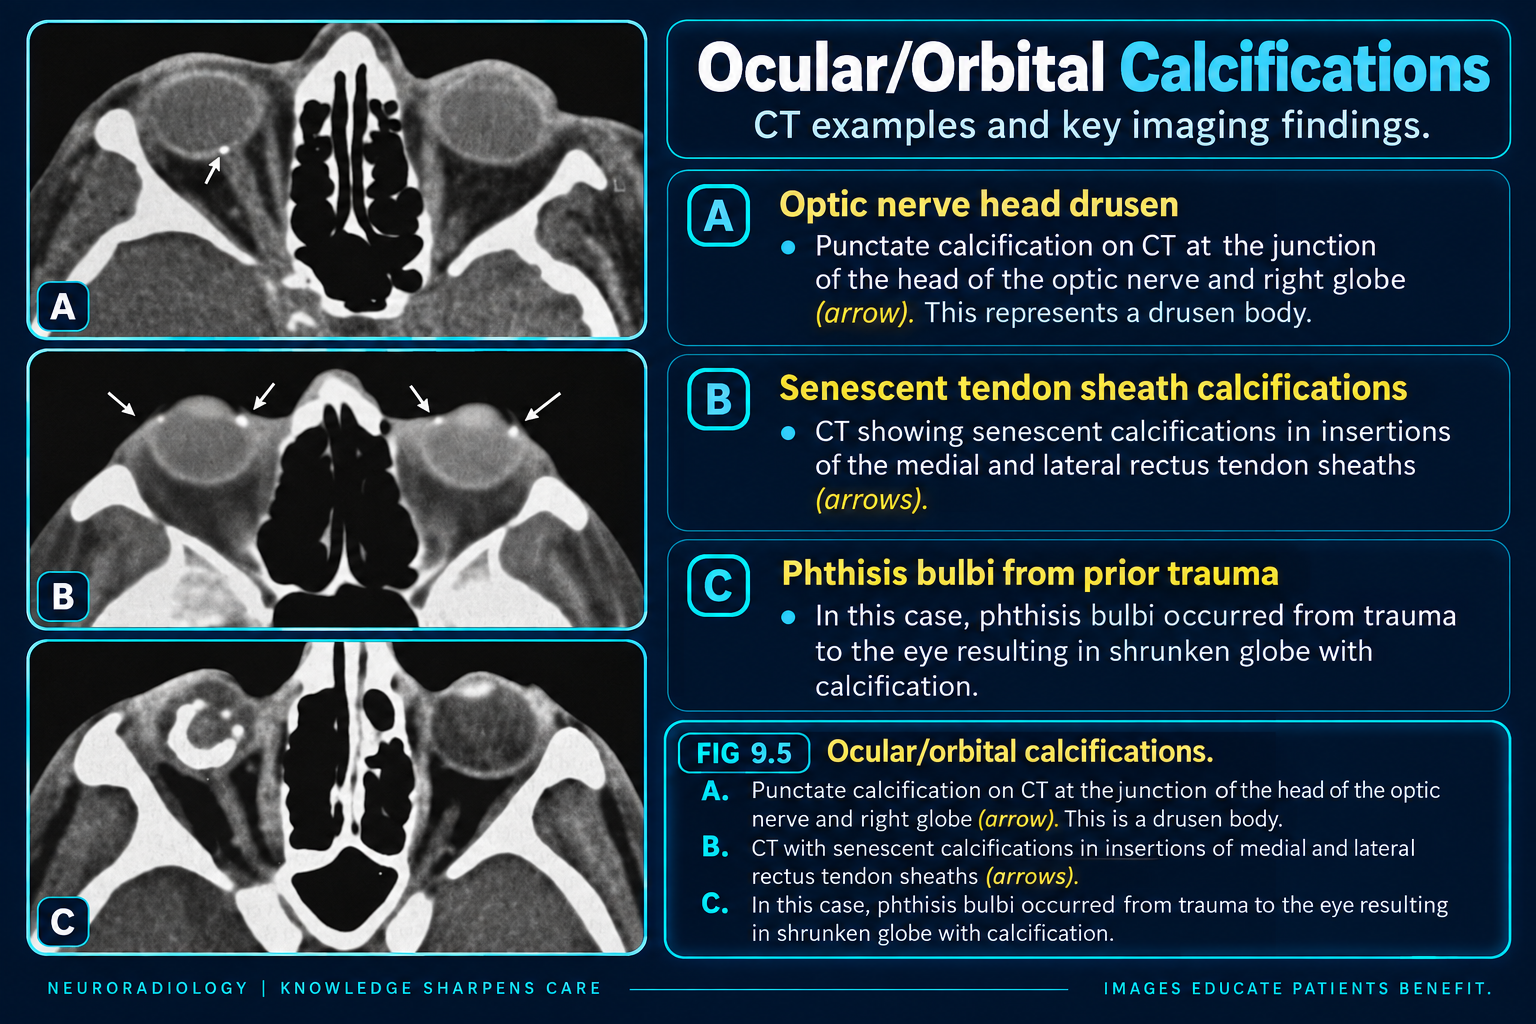
- Anterior scleral plaques: commonly bilateral near the medial and lateral rectus insertions, without a mass.
- Optic disc drusen: punctate focus at the optic nerve head; funduscopic examination, ultrasound, or OCT may confirm.
- Calcified cataract: curvilinear or dense lens mineralization; assess lens position, globe integrity, and trauma history.
Sclerochoroidal
- Idiopathic or age related: typically bilateral, multifocal plaque-like calcium along the posterior eyewall.
- Metastatic calcification: consider hyperparathyroidism, pseudohypoparathyroidism, renal disease or renal tubular disorders, hyperphosphatemia, vitamin D excess, and sarcoidosis.
- Dystrophic calcification: damaged tissue calcifies despite normal calcium-phosphate metabolism.
- Phthisis bulbi: a small deformed globe with coarse calcification after severe trauma, infection, inflammation, surgery, or chronic retinal detachment.
- Senile calcific scleral plaques and scleromalacia perforans.
When metabolic correlation helpsFor unexpected, extensive, bilateral, or early-onset sclerochoroidal calcification, consider calcium, phosphorus, magnesium, renal function, parathyroid hormone, and vitamin D as clinically appropriate.
Masses, Vascular Lesions and Reporting
Mass or orbital lesion
- Optic nerve sheath meningioma: enhancing sheath, tram-track calcification, and possible optic-canal hyperostosis.
- Venous or venolymphatic malformation: rounded phleboliths, enhancement, venous continuity, Valsalva enlargement, or fluid-fluid levels.
- Dermoid: fat-containing superolateral cyst with rim calcification and smooth osseous scalloping.
- Lacrimal epithelial tumor: calcification with infiltration, pain, bone destruction, or perineural spread increases concern for malignancy.
- Amyloidosis: punctate or coarse calcification in an infiltrative lacrimal, muscular, conjunctival, or diffuse orbital process.
- Osseous origin: distinguish matrix mineralization, ground-glass change, trabeculation, or hyperostosis from a primary soft-tissue calcification.
Diagnostic workflow
- Confirm calcium on thin-section CT and bone windows; distinguish blood, dense protein, retained contrast, and foreign material.
- Localize to lens, eyewall, optic disc, optic nerve sheath, intraconal or extraconal space, lacrimal gland, muscle, trochlea, wall, or sinus.
- Describe punctate, plaque-like, curvilinear, laminated, coarse, osseous, or phlebolithic morphology.
- Record any enhancing mass, fat, cystic component, hemorrhage, vascular continuity, perineural spread, or intracranial extension.
- Assess bone for smooth remodeling, hyperostosis, aggressive destruction, or a mineralized matrix.
Pediatric emergency patternA calcified enhancing intraocular mass in a young child is highly concerning for retinoblastoma and warrants urgent ophthalmologic/ocular-oncology evaluation with dedicated orbital and brain MRI for staging.
Sources
Primary Differential
- Calcification of the globe differential, revised by Tariq Walizai on 7 Jul 2024.
- Globe opacification differential: consider intraocular silicone oil treatment.
Related Local References
Interpretive Principle
Location firstLocation is more discriminating than calcium alone. Benign calcifications have stereotyped sites; calcium within an untreated lymphoma or an acute inflammatory lesion is distinctly atypical.